


Page 94 - Portuguese Journal - SPORL - Vol 61. Nº1
P. 94
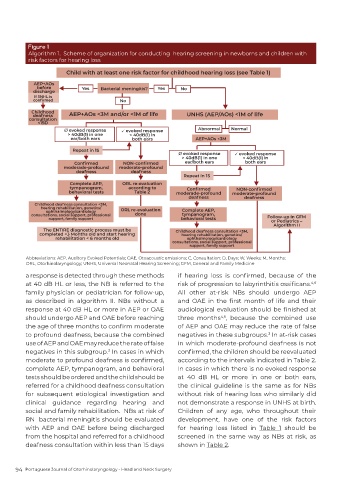
Figure 1
          Algorithm 1.  Scheme of organization for conducting  hearing screening in newborns and children with
          risk factors for hearing loss


          Abbreviations: AEP, Auditory Evoked Potentials; OAE, Otoacoustic emissions; C, Consultation; D, Days; W, Weeks; M, Months;
          ORL, Otorhinolaryngology; UNHS, Universal Neonatal Hearing Screening; GFM, General and Family Medicine
          a response is detected through these methods      if  hearing  loss  is  confirmed,  because  of  the
          at 40 dB HL or less, the NB is referred to the    risk of progression to labyrinthitis ossificans.
                                                                                                        4,6
          family physician or pediatrician for follow-up,   All other at-risk NBs should undergo AEP
          as described in algorithm II. NBs without a       and  OAE  in  the  first  month  of  life  and  their
          response at 40 dB HL or more in AEP or OAE        audiological evaluation should be finished at
          should undergo AEP and OAE before reaching        three months , because the combined use
                                                                          4,6
          the age of three months to confirm moderate       of AEP and OAE may reduce the rate of false
          to profound deafness, because the combined        negatives in these subgroups.  In at-risk cases
                                                                                          3
          use of AEP and OAE may reduce the rate of false   in which moderate-profound deafness is not
          negatives in this subgroup.  In cases in which    confirmed, the children should be reevaluated
                                     3
          moderate to profound deafness is confirmed,       according to the intervals indicated in Table 2.
          complete AEP, tympanogram, and behavioral         In cases in which there is no evoked response
          tests should be ordered and the child should be   at 40 dB HL or more in one or both ears,
          referred for a childhood deafness consultation    the clinical guideline is the same as for NBs
          for subsequent etiological investigation and      without risk of hearing loss who similarly did
          clinical guidance regarding hearing and           not demonstrate a response in UNHS at birth.
          social and family rehabilitation.  NBs at risk of   Children  of  any  age,  who  throughout  their
          RN  bacterial meningitis should be evaluated      development, have one of the risk factors
          with  AEP  and  OAE  before  being  discharged    for hearing loss listed in  Table 1 should be
          from the hospital and referred for a childhood    screened in the same way as NBs at risk, as
          deafness consultation within less than 15 days    shown in Table 2.


      94  Portuguese Journal of Otorhinolaryngology - Head and Neck Surgery

